AI app for healthcare · no coding needed
Clinic room turnover capacity lab
Find operational improvements without shortening required care or cleaning.
Made for: Ambulatory operations managers
What it does for you
The problem
Room turnover procedures create avoidable idle gaps.
What it gives you
Operations-and-clinical-team-reviewed turnover pilot
What you give it
Aggregate room timestampsstaff-approved procedures
How it works, step by step
- Model administrative turnover stages
- Simulate staffing options
- Compare validated capacity changes
- Compare the reviewed result with the recorded baseline and value assumptions
- Capture corrections and named-owner approval before consequential use
- Export a versioned operations-and-clinical-team-reviewed turnover pilot with source references and unresolved questions
Build it yourself with your AI system
Build this app yourself, no coding needed
Start with a quick version you can try in a few minutes. Like it? Then build the full app by copying and pasting our step-by-step instructions: everything is prepared for you.
Sign in to see how to build it yourself
Build a quick version to try, or get the full app pack for Clinic room turnover capacity lab with the step-by-step building instructions. You don't need any technical skills: you copy, paste and answer a few questions. Both are included in the membership.
4 Have it built for you days to a few weeks
Rather not do it yourself, or want it fully tailored to your data, your way of working and your brand? Nexibeo builds Clinic room turnover capacity lab with you.
What's in the app pack
Included in the Complete AI Training membership.
- The building instructions your AI follows, step by step
- The questions your AI will ask you about your business before it starts
- A clickable demo you can open in your browser, to see how it should work
- A detailed blueprint of the screens, the information it keeps and the checks it runs
Become a member to get the app packAlready a member? Sign in
The files, for the technically curious
- START-HERE.mdHow to build it with your own AI (read first)3 KB
- README.mdOverview and links1 KB
- questions.mdQuestions to answer before you build3 KB
- prompt-cloudflare.mdThe full build prompt, hosted on Cloudflare27 KB
- prompt-vps.mdThe same build on your own server (Docker)27 KB
- spec.jsonData model, API, AI pipeline, acceptance criteria14 KB
- demo/index.htmlThe working demo on sample data198 KB
Questions
Do I need to know how to code?
No. You copy and paste the prompts on this page into ChatGPT or Claude, and the AI does the building. When it asks you something, you answer in your own words.
What does it cost?
The quick version, the app pack and the step-by-step instructions are for members: you pay the membership price, not a price per app (see the plans). Building the full app uses your own ChatGPT or Claude subscription. Putting it online is often cheap or no cost at the start, and your AI tells you before anything costs money.
How long does it take?
The quick version: about two minutes. The real app: an afternoon for a first version you can use, longer if you want every feature.
Can I change it to fit my business?
Yes. Tell your AI what to change in plain words, like “add a column for the price” or “use our logo and colours”. Or have Nexibeo build and customise it for you.
More detailsHow the AI works, safeguards and what to build first
Find operational improvements without shortening required care or cleaning
Confirm the buyer's problem and scope, collect aggregate room timestamps and staff-approved procedures, then follow this sequence: 1. Model administrative turnover stages. 2. Simulate staffing options. 3. Compare validated capacity changes. Resolve uncertain cases with qualified reviewers, approve operations-and-clinical-team-reviewed turnover pilot, and measure completed capacity gained minus added staffing and quality-control cost against a documented baseline.
How the AI works
Use AI to interpret permitted inputs, suggest structured mappings and generate candidate outputs for the three stated task modules. Use deterministic code for arithmetic, schema validation, hard constraints and reproducible tests. Review source-linked explanations and uncertainty before accepting results. Simulation only; qualified staff retain infection-control and care constraints. A model suggestion is never a verified fact, professional decision or authorization to act.
Safeguards
Begin with administrative scope or clinician-reviewed material. Minimize sensitive patient data, restrict access and obtain required organizational review before connecting clinical systems. Simulation only; qualified staff retain infection-control and care constraints. Keep all consequential actions under authorized human control and do not fabricate missing inputs, permissions, professional judgments or market evidence.
What to build first
Pilot scope: Simulation only; qualified staff retain infection-control and care constraints. Implement one approved input format, a bounded representative case set and the first two task modules: model administrative turnover stages; simulate staffing options. Support the third module with operator review: compare validated capacity changes. Include source references, corrections, basic organization access, approval states, export and value measurement. Use managed operator assistance for unresolved exceptions. The cost estimate covers this narrow prototype, not unrestricted multi-tenant scale, complex production integrations, specialist certification or physical operations.
What it can connect to
Clinic-approved content and administrative exports. Clinical integrations require separate assessment. Learning portals, calendar scheduling and authorized session exports. Make recording, sharing and retention controls explicit in the product. Start with authorized file exchange. Validate current provider access, usage rights and schema behavior before promising a connector.
The screens in detail
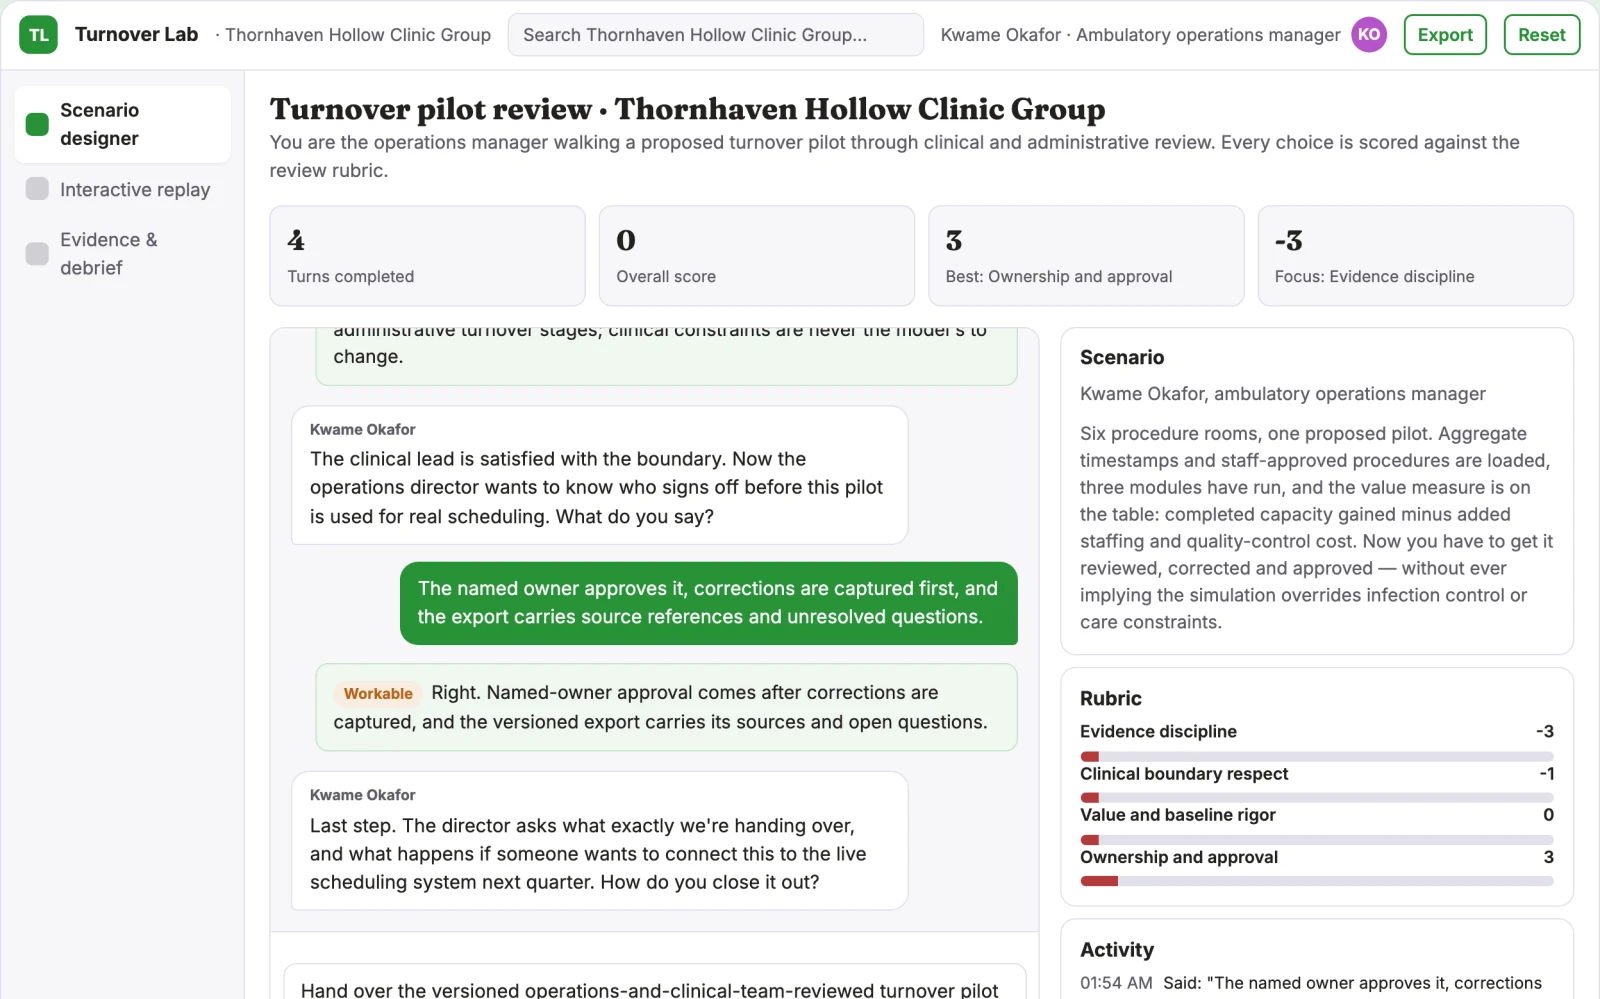
Primary screens: Scenario designer, Interactive replay, Evidence and debrief. Use a scenario catalog with clear goals and difficulty settings. The main session area supports text, optional voice and visible context. Follow it with a replay or decision map, annotated feedback and a next-practice plan. Facilitators can author scenarios and review participant-selected sessions. Make the task-specific outcome operations-and-clinical-team-reviewed turnover pilot visible beside its evidence, review state and value baseline.